 comparison
FDA De Novo vs 510(k): Pathway Selection Guide
Table of Contents
- FDA De Novo vs 510(k): Core Differences
- Understanding 510(k) Submission Requirements and Substantial Equivalence
- FDA De Novo Classification Request: When and Why
- Timeline and Evidence Expectations: De Novo Submission Timeline Compared
- Pathway Selection: A Decision Framework
- Common Pitfalls and What Happens After Clearance
- Conclusion
- Frequently Asked Questions
Last Updated: October 12, 2026
FDA De Novo vs 510(k): Core Differences
Understanding De Novo vs 510k distinction shapes your regulatory timeline, evidence burden, and market access strategy, the first critical decision any medical device company faces.
Here's the core difference: a 510(k) submission demonstrates that your device is substantially equivalent to a legally marketed predicate device already on the market.
This distinction determines how much clinical evidence you'll need, how long review takes, and whether you can proceed.
The 510(k) pathway is generally faster because you're using existing FDA precedent.
Understanding 510(k) Submission Requirements and Substantial Equivalence
A 510(k) submission rests on one core principle: substantial equivalence to a legally marketed predicate device in intended use and technological characteristics.
"Substantial equivalence" doesn't mean identical, it means the same function, patient population, and comparable technology, even if the implementation differs.
The Role of the 510(k) Predicate Device
Your predicate device anchors your entire 510(k) submission. It's a legally marketed device FDA has already cleared or approved.
Choosing the right predicate is deceptively important.
The predicate doesn't have to be identical, just appropriate for comparison. A glucose monitor's predicate should be another glucose monitor, not a general diagnostic device.
Many companies underestimate predicate selection, picking something somewhat similar and hoping it works.
FDA De Novo Classification Request: When and Why
When no appropriate 510(k) predicate exists, the De Novo pathway becomes necessary, when your device is genuinely novel, technologically or in intended use.
A De Novo classification request asks FDA to establish a new device classification for your product category.
De Novo is appropriate when:
- Your device uses new technology with no legally marketed equivalent
- Your device targets a new patient population or indication
- Your device combines technologies in a way that creates a new regulatory category
De Novo typically results in a Class II or Class III classification. Once granted, your device becomes the predicate for future competitors, an advantage (you own the regulatory pathway) and a responsibility (your classification sets the standard).
Timeline and Evidence Expectations: De Novo Submission Timeline Compared
Timelines for 510(k) and De Novo submissions are often quoted as single numbers, which is misleading. What matters is the split between FDA review time (the clock that starts when FDA accepts your submission) and total time to clearance, which includes preparation, pre-submission interactions, and AI holds.
FDA review clocks vs. real-world timelines
For a traditional 510(k), FDA's statutory review goal under MDUFA is 90 FDA days for substantive review, not 90 calendar days, and not your total project timeline. In practice:
- FDA review clock: roughly 90 FDA days for a clean traditional 510(k).
- Calendar time from submission to clearance: commonly 3-6 months, longer when FDA issues an AI request that pauses the clock.
- Preparation time: typically 2-6 months, longer if you need bench data, software documentation, or a usability study.
For a De Novo, the review goal is longer and variance wider:
- FDA review clock: FDA's MDUFA goal for a De Novo request is 150 FDA days, a target, not a guarantee.
- Calendar time from submission to grant: commonly 6-12 months, and 12-18 months when clinical data, a new special controls proposal, or a classification panel review is involved.
- Preparation time: often 6-18 months, because you are generating the evidence that will define the new device type.
A practical rule: treat the FDA review clock as the floor, not the plan. Build your schedule around total calendar time, and add buffer for at least one AI cycle.
Why the De Novo clock is longer
The De Novo review is not just a longer 510(k). FDA evaluates whether your device is safe and effective and decides how the device type should be classified going forward, drafting the classification regulation and special controls for future devices. That work drives the longer review goal.
Evidence expectations, pathway by pathway
The evidence burden is where the two pathways diverge most sharply. A useful way to think about it is by evidence type:
| Evidence type | 510(k), typical expectation | De Novo, typical expectation |
|---|---|---|
| Bench / performance testing | Required; scope driven by the predicate and any recognized consensus standards | Required; scope driven by FDA's view of what is needed to establish safety and effectiveness for a new device type |
| Software / cybersecurity documentation | Required if the device contains software; level of concern drives depth | Required; often more extensive because there is no predicate to anchor the expected documentation |
| Human factors / usability | Required when use error could cause harm; often a formative study plus a summative validation | Frequently required; FDA may expect a summative human factors study as part of the safety and effectiveness case |
| Clinical data | Sometimes required; often limited to a focused endpoint or a literature-based argument | Frequently required; may include a prospective clinical study, and FDA may expect a defined endpoint and follow-up |
| Biocompatibility | Required for patient-contacting materials; ISO 10993 series is the common reference | Required; same framework, but FDA may ask for additional characterization if the material or contact duration is novel |
| Sterilization / shelf life | Required if applicable; validated per recognized standards | Required; same framework, but FDA may scrutinize the validation more closely for a new device type |
Two implications follow. First, if your device is software-heavy, the 510(k) path can still be substantial, software documentation and cybersecurity are not trivial even with a predicate. Second, if your device is novel in intended use, De Novo will almost always require clinical evidence; plan for that before you file.
Fees and the fee-year assumption
Both pathways are subject to FDA user fees, which change each fiscal year. The 510(k) fee is lower than the De Novo fee, and both are lower for qualifying small businesses. Pull the current schedule from FDA's website and note its fiscal year rather than relying on a number quoted in a blog post.
A note on pre-submission time
Neither the 90-day nor the 150-day review clock includes Q-Submission (Q-Sub) time. A Pre-Sub is often the highest-leverage step for a De Novo, aligning you and FDA on the evidence package before you commit. Budget 2-4 months for a Pre-Sub cycle.
Pathway Selection: A Decision Framework
Choosing between De Novo and 510(k) requires a structured evaluation:
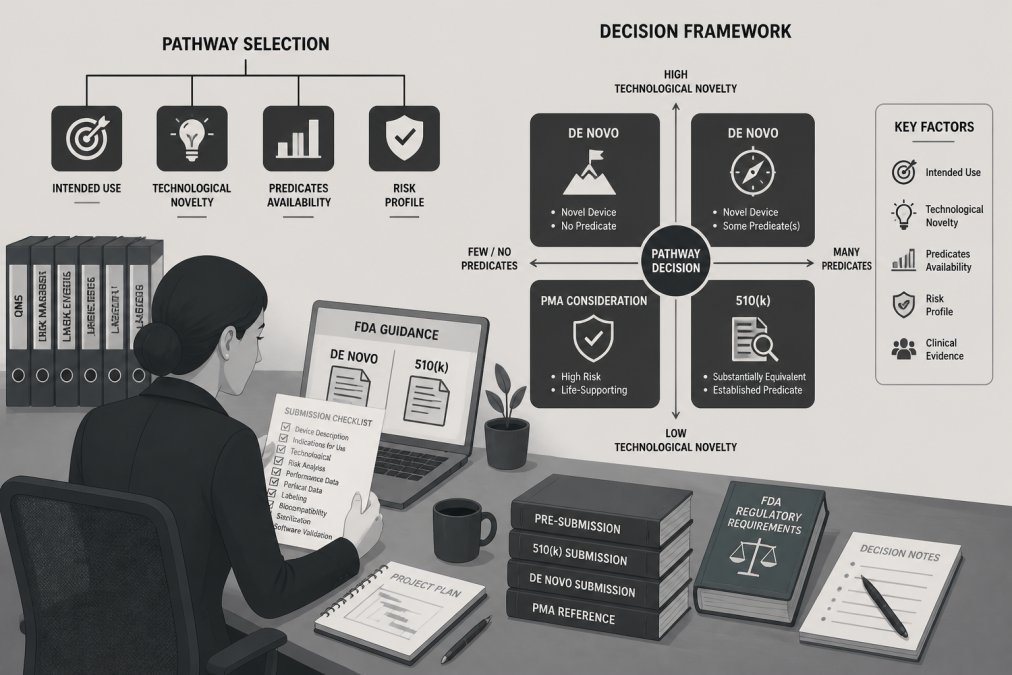
Step 1: Identify potential predicates. Search FDA's 510(k) and device classification databases for similar devices, comparing intended use, technology, patient population, and indications. Multiple reasonable matches suggest a viable 510(k); none or weak matches suggest De Novo.
Step 2: Evaluate substantial equivalence. For each potential predicate, assess whether your device is substantially equivalent in intended use and technological characteristics.
Step 3: Consider device risk and complexity. Higher-risk (Class III) devices may be difficult to clear via 510(k) because FDA may question whether substantial equivalence suffices.
Step 4: Assess evidence availability. A 510(k) typically requires nonclinical data and sometimes limited clinical data; a De Novo requires more comprehensive evidence, often including clinical trials.
Common Pitfalls and What Happens After Clearance
The pitfalls that derail 510(k) and De Novo submissions are rarely about the science. They are about process: what FDA expects in the submission, how the review clock works, and what happens after a decision.
Refuse-to-Accept (RTA) and the acceptance review
Before substantive review, FDA performs an acceptance review. If your submission is missing required elements, the correct user fee, a complete FDA Form 3514 for a 510(k), or required De Novo content, FDA can issue a Refuse-to-Accept (RTA) decision.
The most common RTA triggers are administrative: wrong fee amount, missing signature, incomplete device description, or a predicate not actually legally marketed. The fix is checklist-driven submission assembly.
Additional Information (AI) requests and the review clock
Once FDA accepts your submission, the review clock starts. If FDA issues an Additional Information (AI) request, the clock is put on hold until you respond.
The quality of your original submission determines how many AI cycles you face. A submission that anticipates FDA's questions, clear predicate comparison, complete software documentation, well-justified clinical evidence plan, typically sees fewer and shorter holds.
Pre-submission (Q-Sub) interactions
FDA's Q-Submission program is the formal mechanism for pre-filing feedback. The most relevant types are:
- Pre-Submission (Pre-Sub): written feedback and, optionally, a meeting on your proposed submission content, evidence plan, and predicate strategy. This is the single most useful Q-Sub for a De Novo, and valuable for a 510(k) with a borderline predicate.
- Submission Issue Request (SIR): used to discuss a specific issue FDA raised during review, such as a proposed AI response strategy.
- Study Risk Determination: used when you want FDA's view on whether a planned clinical study is significant risk, non-significant risk, or exempt.
A Pre-Sub doesn't guarantee acceptance, but it substantially reduces the risk of an RTA or a first-cycle AI request on a fundamental issue.
What happens after a 510(k) clearance
A 510(k) clearance means FDA has determined your device is substantially equivalent to a legally marketed predicate. You can market immediately, subject to:
- General controls: labeling, establishment registration and device listing, medical device reporting (MDR), and record-keeping.
- Special controls: if your device type is subject to a special controls regulation, you must comply.
- Post-market surveillance: may be required depending on the device type and FDA's determination.
A key point often missed: a 510(k) clearance does not create a new device classification. Your device is cleared under its predicate's existing classification. A competitor can file their own 510(k) using the same predicate, or your device, once legally marketed.
What happens after a De Novo grant
A De Novo grant is different in kind, not just degree. When FDA grants a De Novo request, it:
- Creates a new device classification (typically Class I or Class II, occasionally Class III) with a new regulation number and product code.
- Establishes the special controls that will apply to that device type going forward.
- Makes your device a predicate for future 510(k) submissions by other companies entering the same device type.
That third point is strategic. Once your De Novo is granted, a competitor can file a 510(k) citing your device as the predicate, generally faster and cheaper than their own De Novo.
There's a corresponding responsibility: the special controls in your De Novo order become the compliance baseline for the entire device type. If your evidence package was thin in an area, that thinness can become the standard future devices are held to.
A note on misclassification risk
If you assume your device is Class II and file a 510(k), but FDA views it as higher risk or lacking a valid predicate, you may receive a Not Substantially Equivalent (NSE) decision. Your options then are to file a De Novo, file a PMA, or argue the NSE. The cost isn't just lost review time, it's reframing your entire evidence package for a different pathway.
Conclusion
Selecting the right FDA pathway through De Novo vs 510k is a strategic decision that shapes your regulatory timeline, evidence requirements, and market entry.
At E & E Medicals and Consulting, we help medical device companies navigate both pathways with clarity and confidence.
Ready to clarify your pathway and accelerate your market access? Contact E & E Medicals and Consulting to discuss your device's regulatory strategy and get started with a pre-submission consultation.
| Pathway | Timeline | Evidence Burden | Best For | Key Requirement |
|---|---|---|---|---|
| 510(k) | 90 days - 6 months | Nonclinical; limited clinical | Devices with appropriate predicates | Substantial equivalence to predicate |
| De Novo | 6-18 months | Comprehensive nonclinical and clinical | Novel devices; new categories | Safety and effectiveness demonstration |
Frequently Asked Questions
What is the main difference between FDA De Novo and 510(k) pathways?
The 510(k) pathway requires demonstrating substantial equivalence to an existing legally marketed predicate device. De Novo is for novel devices with no appropriate predicate. 510(k) submissions typically take 90 days for standard review or 30 days for expedited review. De Novo submissions take approximately 150-180 days. De Novo establishes the device classification for the first time; once granted, subsequent similar devices may use 510(k) with the De Novo device as a predicate.
When should I use the De Novo pathway instead of 510(k)?
Use De Novo when your device is genuinely novel and no appropriate 510(k) predicate device exists in the marketplace. This occurs when your device has a new intended use, new technological characteristics, or a new combination of known features that distinguish it from existing cleared devices. De Novo is also appropriate when you cannot demonstrate substantial equivalence despite searching for predicates. If a predicate exists and your device is substantially equivalent, 510(k) is faster and more cost-effective.
What evidence is required for a De Novo submission?
De Novo submissions require clinical and nonclinical data demonstrating safety and effectiveness. Nonclinical testing includes bench testing and performance data relevant to your device's intended use. Clinical evidence may involve clinical trials, literature review, or real-world data depending on risk classification. You must also provide risk analysis under ISO 14971, design history documentation, and manufacturing controls. The FDA will propose a classification (Class I, II, or III) based on your evidence and the device's risk profile and intended use.
Can a device approved through De Novo be used as a predicate for a 510(k)?
Yes. Once a De Novo device is cleared and classified, it becomes a legally marketed device and can serve as a predicate for subsequent 510(k) submissions. This allows follow-on manufacturers or product variants to use the streamlined 510(k) pathway by demonstrating substantial equivalence to the De Novo device. This pathway is sometimes called a 510(k) following De Novo approval and significantly reduces time to market for similar products.
What happens if my 510(k) submission cannot find a suitable predicate device?
If you cannot identify an appropriate predicate device after thorough searching, you cannot proceed with a standard 510(k). You have two options: pursue a De Novo pathway to establish a new classification, or explore a reclassification petition if you believe the device should be Class I or II rather than Class III. Some companies also consult with the FDA through a Pre-Submission meeting to clarify pathway eligibility and predicate acceptability before formal submission.
EXTERNAL CITATIONS VERIFICATION:
- FDA 510(k) Database, for predicate device identification and substantial equivalence framework
- FDA De Novo Classification Pathway Guidance, for De Novo process and evidence requirements
- FDA Device Classification Regulations, for risk classification and regulatory requirements


